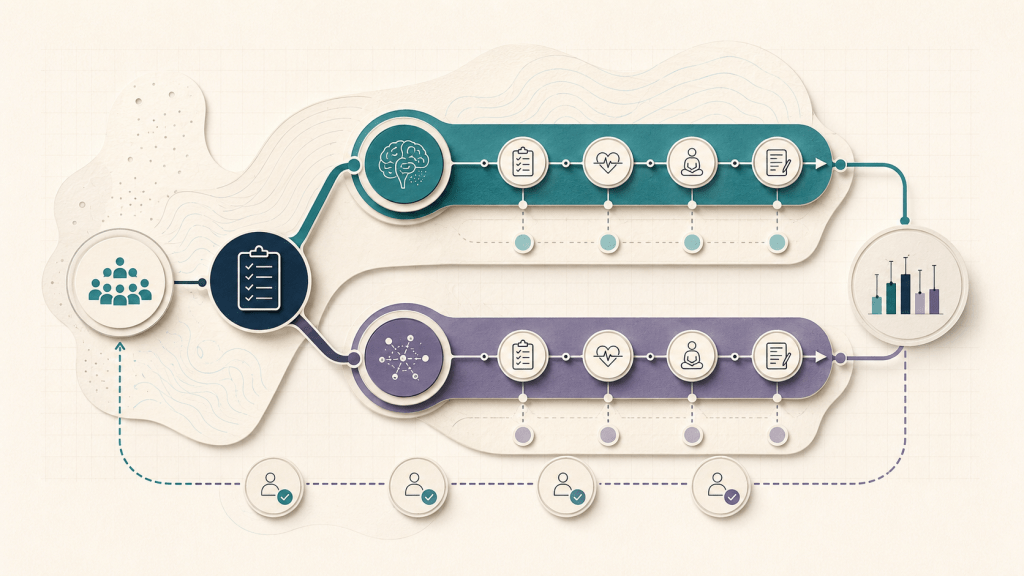
A psychedelic clinical trial is not simply a group of people taking a substance and reporting how they feel. It is a tightly defined research programme designed to separate a treatment signal from expectation, attention, natural change and bias.
The strongest trials pre-specify their questions, screen participants, standardise the investigational product and support model, compare outcomes between groups and monitor safety over time. Psychedelic effects add distinctive challenges—but the evidentiary standard remains the same as for other medicines.
ARTICLE AT A GLANCE
01
Trials answer narrow questions
Each phase has a defined purpose. A positive result at one stage does not complete the development pathway.
02
The whole protocol matters
Drug dose, preparation, session support, setting and follow-up can all influence outcomes and must be described.
03
Blinding is unusually difficult
Noticeable psychoactive effects may reveal allocation, making expectancy assessment and independent ratings important.
In this guide
From laboratory work to clinical development
Before larger patient trials, researchers establish product quality, pharmacology and a safety rationale. Early human studies may examine tolerability, dose and short-term effects. Later studies ask whether an intervention benefits a defined population and whether those benefits outweigh its risks.
Clinical development is cumulative. Phase 1 generally focuses on safety and pharmacology; phase 2 explores dose and preliminary efficacy; phase 3 aims to confirm benefits and characterise harms in a larger group. Regulators assess the full package, including manufacturing and trial conduct—not a single headline result.
Eligibility and screening
A protocol defines who can take part. Screening may consider diagnosis, symptom severity, physical health, medicines, substance use and mental health history. These decisions protect participants and reduce confounding, but they also narrow generalisability.
When reading a trial, compare the enrolled group with the wider population that might eventually seek treatment. Results from carefully selected volunteers do not automatically apply to people with different diagnoses, co-existing conditions or medication profiles.
Randomisation and control groups
Random assignment helps make groups comparable before treatment. A control may be an inactive placebo, a low dose, an active comparator or the same psychological support without the investigational drug. The choice affects what the trial can conclude.
If every participant receives intensive preparation and follow-up, the study may estimate the effect of adding the drug to that package. It may not reveal how much benefit came from the substance, the support, their interaction or the clinical environment.
Preparation, dosing sessions and follow-up
Many psychedelic protocols involve preparation before dosing, supervised sessions and later meetings sometimes described as integration. These components are not interchangeable across studies. The number, duration, training model and therapeutic intent should be reported clearly.
Standardisation matters for reproducibility and safety. At the same time, interpersonal support is difficult to blind and may vary between practitioners. Researchers therefore need treatment manuals, fidelity checks and procedures for reporting boundary or safeguarding concerns.
Functional unblinding and expectancy
In an ordinary blinded trial, participants and investigators should not know the assignment. With a conspicuously psychoactive drug, many people can infer it. Prior experience, publicity and preferences may strengthen expectations.
Regulatory guidance highlights this problem. Useful safeguards include credible controls, asking participants and staff which allocation they believe occurred, using independent or central outcome raters and analysing how guesses relate to outcomes. These methods reduce uncertainty; they cannot always remove it.
Outcomes, statistics and clinical meaning
Trials designate a primary outcome and time point in advance. Symptom scales are common, but readers should also look for functioning, quality of life, relapse, additional treatment and patient-important harms. A statistically detectable difference is not automatically a meaningful one.
Sample size calculations, missing-data rules and analysis plans should be set before unblinding. Confidence intervals show the range of effects compatible with the data. Subgroup claims usually require caution unless planned and adequately powered.
Safety monitoring and long-term evidence
During and after dosing, trials may monitor vital signs, acute psychological distress, adverse events, serious events and withdrawal. Good reporting explains how events were elicited and whether assessors attributed them to the drug, support or other causes.
Uncommon or delayed harms may not appear in small, short studies. Regulators can require larger trials, longer follow-up or post-authorisation monitoring. Approval is a judgement about a particular product, indication, dose and delivery model—not a blanket endorsement of a substance category.
What a well-designed trial can tell us
A rigorous trial can estimate whether a defined intervention outperformed a defined comparison for a defined group over a defined period. That is valuable—and deliberately narrower than “psychedelic therapy works.”
The clearest reporting keeps the drug, psychological support, expectancy, safety systems and follow-up visible, so readers can understand exactly what was tested.
Safety and scope
Trial participation is not equivalent to treatment and should only occur through an appropriately approved study with informed consent and clinical oversight. A research protocol’s screening and monitoring cannot be recreated through unsupervised use.
ARTICLE RECORD
- Editorial category: Evidence & Research
- Evidence status: Foundational trial-design guide informed by current regulatory guidance
- Sources checked: 29 July 2026
- Independent clinical review: Not currently listed
Sources and further reading
- FDA: Psychedelic Drugs—Considerations for Clinical Investigations — final US regulatory guidance published in 2026
- UK Parliament POST: Psychedelic-assisted therapy — UK policy briefing on evidence, regulation and delivery considerations
- ClinicalTrials.gov — public registry for study protocols, status and results
- Muthukumaraswamy et al. (2021) — blinding and expectancy in psychedelic randomised controlled trials
- Wen et al. (2024) — systematic review of placebo and blinding approaches
Editorial note: This article is for education and evidence literacy. It is not medical advice, a diagnosis, a recommendation to use a substance, or a substitute for care from a qualified professional.

